

Knee osteoarthritis (OA) is a condition affecting the whole joint. It can influence the cartilage, underlying bone, joint lining, ligaments and surrounding muscles. It can also change how the knee responds to activity. Its most recognisable features are pain related to activity, stiffness after rest and gradually increasing difficulty with activities such as standing from a chair, walking, climbing stairs or exercising.
It can affect people with very different lifestyles. Some have spent years doing physically demanding work. Some have previously injured their knee. Some are active runners or former athletes, while others have become less active because of work, illness or pain.
Knee OA usually develops through an interaction of factors rather than one single cause. These can include increasing age, previous knee injury, genetics, joint anatomy, muscle capacity, occupational exposure, physical activity patterns and metabolic health. Higher body weight is associated with greater knee OA risk, but it should be understood as one contributing factor, not a personal failure or the sole explanation for someone’s symptoms.
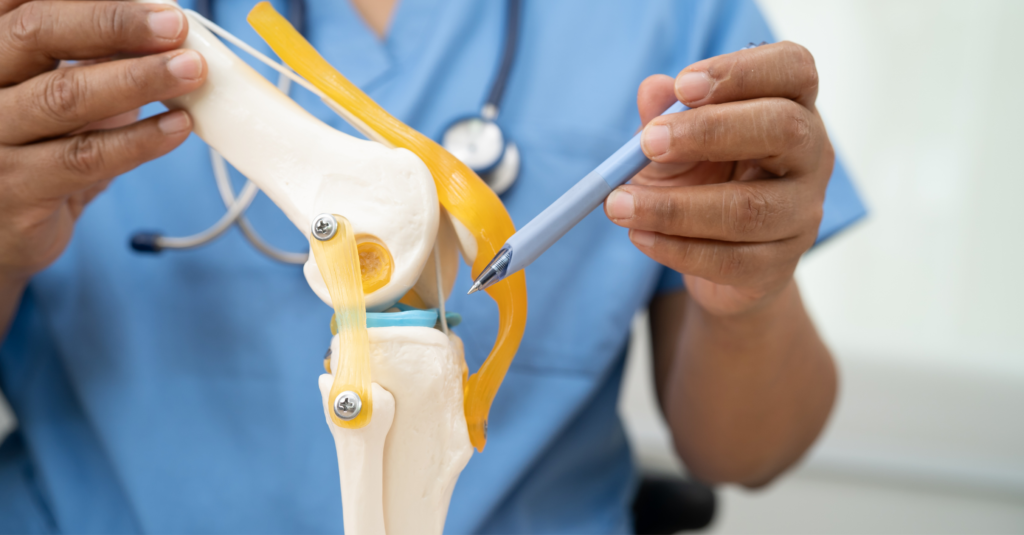
What does OA feel like?
Knee OA commonly causes pain during or after activities such as walking, standing, climbing stairs, squatting or rising from a chair. Symptoms may vary from day to day according to activity, recovery, sleep and general health.
Stiffness is also common after the knee has been still for some time. You may notice it first thing in the morning, after driving or when standing up from your desk. With OA, this stiffness usually begins to settle as you move and commonly lasts less than 30 minutes.
A typical clinical pattern includes:
- Being 45 or older.
- Knee pain caused or aggravated by activities such as walking, standing, using stairs, squatting or rising from a chair.
- Stiffness after prolonged rest, including sleeping, sitting, driving or working at a desk.
- Morning stiffness that usually lasts less than 30 minutes.
- A knee that begins to loosen with gentle movement.
- Reduced strength or increasing difficulty with everyday tasks.
You may also notice crepitus: a grating, crunching, clicking or crackling sensation when the knee moves. This is common in knee OA, but noise alone does not necessarily indicate damage or mean that movement is unsafe, particularly when there is no pain or swelling.
These features can support a clinical diagnosis, but not every painful or noisy knee is osteoarthritis. A proper assessment should consider how the symptoms began, previous injuries, swelling, strength, balance, general health and which activities are becoming difficult.
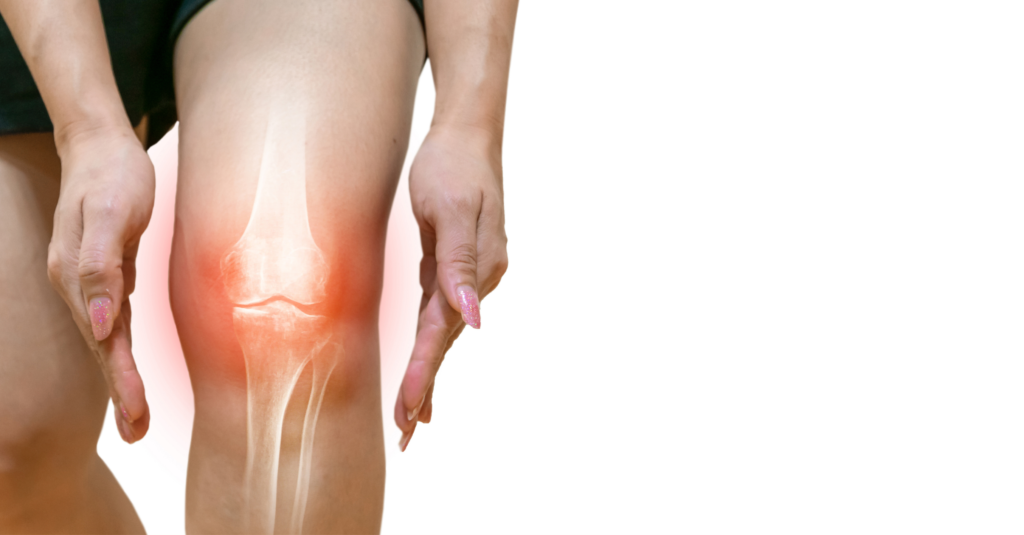
Who gets knee OA?
Knee OA becomes more common with age, particularly from the mid-40s onwards, but it is not exclusively a condition of later life. A younger person may develop it following a significant knee injury, while someone much older may have relatively few symptoms.
Previous injury is one of the clearest reasons OA may be identified earlier. An ACL rupture, meniscal injury, patellar dislocation or fracture can affect the joint at the time of injury. Residual weakness, instability, altered coordination, repeated injury or incomplete rehabilitation may add to the longer-term risk.
Work can matter too. Years of frequent kneeling, squatting, climbing or heavy lifting may expose the knees to repeated high demands. At the other end of the spectrum, stationary work may provide very little movement variety. Remaining seated, or standing almost motionless at a desk, for hours can contribute to stiffness and reduced physical conditioning.
Women develop knee OA more frequently, particularly later in life. Family history, genetics and joint shape may influence susceptibility, while diabetes, gout and other metabolic or joint conditions can form part of the wider picture.
No single factor tells the whole story. Two people may have similar changes on an X-ray but very different symptoms, strength and activity levels.
Body weight and activity
People with a higher body weight are often given a blunt instruction to lose weight. That advice can feel dismissive and may overlook the reason they sought help in the first place: their knee hurts and activity has become harder.
Body weight does not tell you how active, strong or healthy someone is. It cannot explain their knee pain on its own.
A higher body weight can increase the cumulative demand placed on the knee, while body composition and metabolic factors may also influence joint health. At the same time, knee pain can lead to less activity, reduced strength and poorer conditioning. Cause and consequence can become difficult to separate.
Exercise should not be postponed until someone loses weight. A more useful starting question is:
What can my knee manage now, what do I want it to manage in the future, and how can I bridge that gap safely?
This shifts the focus towards confidence, strength and useful activity. Weight and metabolic health can still be discussed sensitively when they are relevant to the person’s health and goals.

What does exercise mean?
Exercise for knee OA is the planned use of movement and loading to improve a particular capacity.
An exercise might aim to improve:
- Strength for standing from a chair.
- Control for descending stairs.
- Endurance for longer walks.
- Balance and confidence.
- Knee movement after rest.
- Tolerance for running.
- Capacity for work, gardening or sport.
Before starting an exercise, you should understand:
- What is the exercise intended to improve?
- How does that relate to an activity that matters to you?
- What is the appropriate starting position?
- What response is acceptable during and after it?
- How and when should it be progressed?
Exercise recommendations for OA should be individualised, appropriately dosed and progressively adjusted according to physical function, personal goals, preferences and available support.
How should my knee respond?
Exercise traffic-light guide
| Response | Interpretation | Action |
| Pain 0–2/10, normal movement and no meaningful later reaction | Green | Continue. When this has been well tolerated consistently, consider progressing one variable. |
| Pain 3–5/10, but controlled, without limping, and back to your usual baseline by the following day | Amber—but acceptable | Keep the same dose and monitor the response. Do not progress yet. |
| Pain above 5/10, sharp pain or a feeling of instability, new limping, marked loss of function, increased night or resting pain, swelling, or not back to baseline within approximately 24 hours | Red | Stop or reduce the provoking activity. Adjust the range, resistance, repetitions or walking duration. Seek reassessment if this happens repeatedly. |
The aim is not to make every exercise completely pain-free. It is to find a manageable dose that challenges the knee without causing a substantial or prolonged reaction. Your normal response matters more than achieving a particular pain score.

How progression works
As an exercise becomes comfortable, it may stop providing enough stimulus for further improvement. Progression gives the body a new reason to adapt.
What does that mean:
- Add a few repetitions.
- Increase the resistance.
- Move through a slightly greater range.
- Use less hand support.
- Lower the chair.
- Walk for a little longer.
- Introduce a more demanding version of the movement.
Choose one change, then see how the knee responds. Progress is not always linear; illness, poor sleep, an unusually active week or a flare-up may require a temporary reduction.
That is not failure. It is load management.
When guidance helps
You may benefit from professional help if you are unsure whether your symptoms fit a typical OA pattern, do not know where to begin or have already tried exercises without making progress.
An initial assessment can identify what is limiting you. Is it strength, confidence, balance, mobility, endurance or a combination of several factors? Your programme can then be built around the activities you want to improve rather than a generic diagnosis.
You should gradually become confident enough to manage much of the programme independently. Occasional reviews can still be useful. An exercise that suited you six weeks ago may now be too easy, unnecessarily difficult or no longer relevant.
A review is an opportunity to change course.

The Flow Osteo approach
Flow Osteo can help you understand what your symptoms mean, identify your starting point and build a programme around the activities that matter to you.
Hands-on treatment may help reduce discomfort and make movement easier in the short term. Progressive loading then aims to improve strength, confidence and functional capacity over time.
Treatment may help you move more comfortably today. Progressive loading helps build what you can do tomorrow. At Flow Osteo, we can help with both.
The objective is to help you understand your exercises:
- Why you are doing them.
- What each exercise is intended to change.
- How hard it should feel.
- How your knee should respond.
- When it is time to progress.
- How the programme connects to your life.
Start with a level that you can perform confidently and consistently, understand what each exercise is intended to improve, and progress as your capacity develops.
If you are unsure where to begin, an initial assessment can help you find an appropriate starting point. Follow-up reviews can then help determine whether an exercise should be progressed, adjusted or replaced as your strength, confidence and goals change.
Find your starting point. Understand the purpose. Load progressively. Review your progress. Build towards what matters.
This article provides general information and does not replace an individual diagnosis or exercise prescription. Seek an appropriate clinical assessment if symptoms are severe, rapidly changing or associated with marked swelling, heat, redness, significant trauma, repeated locking or an inability to bear weight.

References
- Moseng T, Vliet Vlieland TPM, Battista S, et al. EULAR recommendations for the non-pharmacological core management of hip and knee osteoarthritis: 2023 update. Annals of the Rheumatic Diseases. 2024;83(6):730–740.
- Holden MA, Metcalf B, Lawford BJ, et al. Recommendations for the delivery of therapeutic exercise for people with knee and/or hip osteoarthritis: an international consensus study from the OARSI Rehabilitation Discussion Group. Osteoarthritis and Cartilage. 2023;31(3):386–396.
- Dhillon J, Kraeutler MJ, Belk JW, et al. Effects of running on the development of knee osteoarthritis: an updated systematic review at short-term follow-up. Orthopaedic Journal of Sports Medicine.2023;11(3):23259671231152900.
- Whittaker JL, Culvenor AG, Juhl CB, et al. OPTIKNEE 2022: consensus recommendations to optimise knee health after traumatic knee injury to prevent osteoarthritis. British Journal of Sports Medicine. 2022;56(24):1393–1405.
- Lim J, Choi A, Kim B. The effects of resistance training on pain, strength, and function in osteoarthritis: systematic review and meta-analysis. Journal of Personalized Medicine. 2024;14(12):1130.


